

Speak to a licensed insurance agent.
1-888-411-7647 | TTY:711
Mon. - Fri. 7:30 am - 5 pm CT
SmartMatch Insurance Agency Logo

Medicare Advantage Open Enrollment Period

Medicare Advantage in 2027: What to Check Before You Choose a Plan

Published October 1, 2026

Four things to check before choosing a 2027 Medicare Advantage plan: doctors and network, prescriptions, copays, and the out-of-pocket limit.

Key takeaways

  • CMS projects the average Medicare Advantage premium will fall from $14.37 in 2026 to $12 in 2027.
  • About 70% of Medicare Advantage plans with Part D coverage list a $0 plan premium, but you generally still pay your Part B premium.
  • The median in-network out-of-pocket limit rose from $6,500 to $7,100 in the CMS landscape file.
  • The average drug deductible in MA-PD plans rose from about $434 to $525.
  • Open Enrollment runs October 15 through December 7, 2026, and changes generally take effect January 1, 2027.

Data checked October 1, 2026. Landscape calculations use the CMS files updated September 30, 2026.

2027 Medicare Advantage plans remain widely available across the nation, but the details inside those plans are changing. Premiums are only one part of the picture. Your plan’s provider network, prescription coverage, copays and annual out-of-pocket limit can have a much larger effect on what you pay and where you receive care.

The Centers for Medicare & Medicaid Services (CMS) projects that the enrollment-weighted average Medicare Advantage premium will decrease from $14.37 in 2026 to $12 in 2027. CMS also says more than 99% of people with Medicare will have access to at least one Medicare Advantage plan, and 97% will have at least 10 choices.

That broad national picture is reassuring. It does not mean your current plan will have the same costs, benefits or network next year.

The number of 2027 Medicare Advantage plans is relatively stable

CMS projects that the national number of available Medicare Advantage plans will remain fairly stable in 2027. Its September announcement estimated approximately 5,532 plans nationwide, compared with 5,553 in 2026.

Our review of the updated CMS landscape file identified 5,522 distinct Medicare Advantage offerings for 2027, down 31 from 2026. The small difference from CMS’s announcement likely reflects the timing and treatment of updates in the downloadable file.
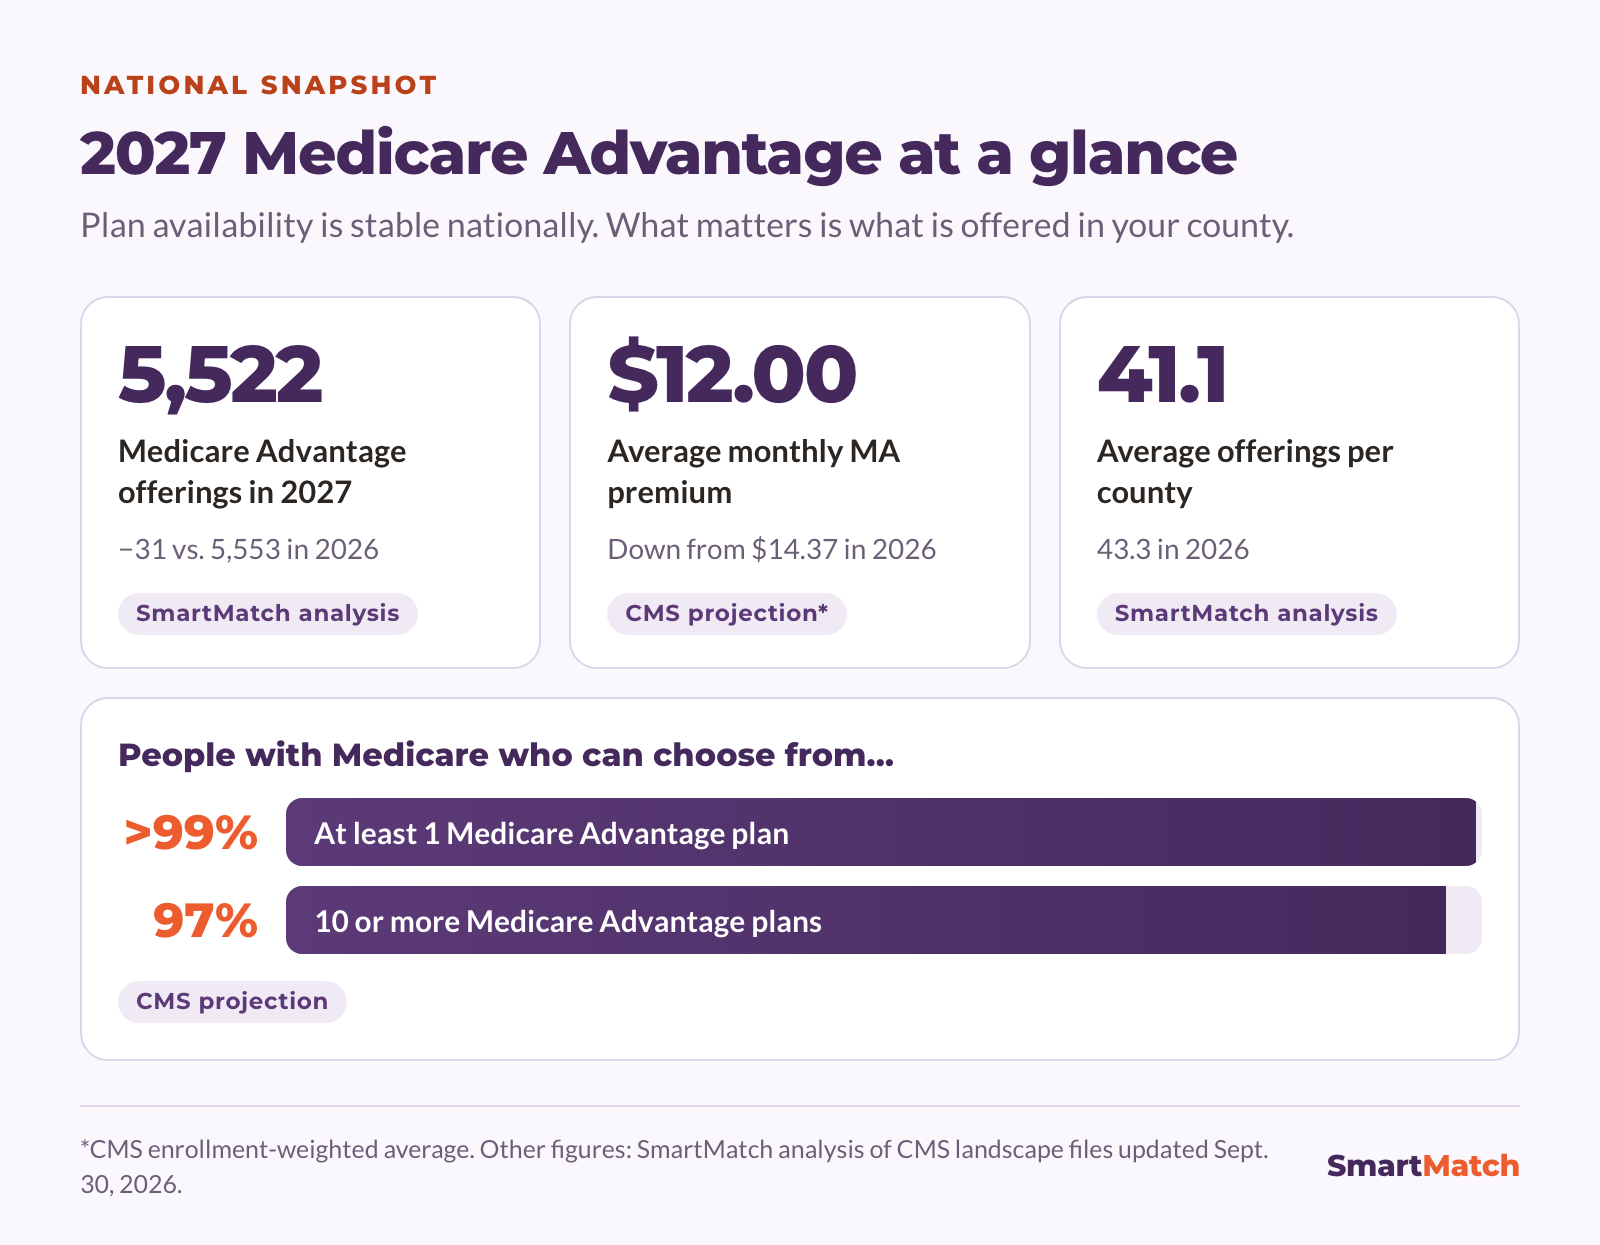
2027 Medicare Advantage at a glance: 5,522 Medicare Advantage offerings in 2027, down 31 from 5,553 in 2026. CMS projects the enrollment-weighted average monthly premium will fall from $14.37 to $12.00. Counties average 41.1 offerings, down from 43.3. CMS says more than 99% of people with Medicare can choose at least one Medicare Advantage plan and 97% can choose 10 or more.
Premium and access figures are CMS projections. Offering counts are SmartMatch calculations from the CMS landscape file.
See the numbers
National Medicare Advantage measure20262027
Distinct MA offerings in the Sept. 30 landscape file5,5535,522
CMS enrollment-weighted average monthly premium$14.37$12.00
County-level average number of offerings43.341.1

What this means for you: National plan availability is stable, but Medicare Advantage is local. Enter your ZIP code in Medicare Plan Finder to see the plans actually available where you live.

Zero-dollar premiums remain common, but premium is not the whole cost

In the updated landscape file, about 70% of Medicare Advantage plans that include Part D coverage list a $0 consolidated plan premium. You must generally continue paying your Medicare Part B premium, and a $0 plan premium does not mean your health care is free.

Look beyond the monthly premium and compare:

  • Primary care and specialist copays
  • Hospital and outpatient costs
  • The in-network maximum out-of-pocket limit
  • Prescription drug deductibles and copays
  • Provider and pharmacy networks
  • Prior authorization rules

CMS estimates that approximately eight in 10 Medicare Advantage enrollees will be able to remain in their current plan with the same or a lower premium in 2027. Even if your premium does not rise, other costs or benefits may change.
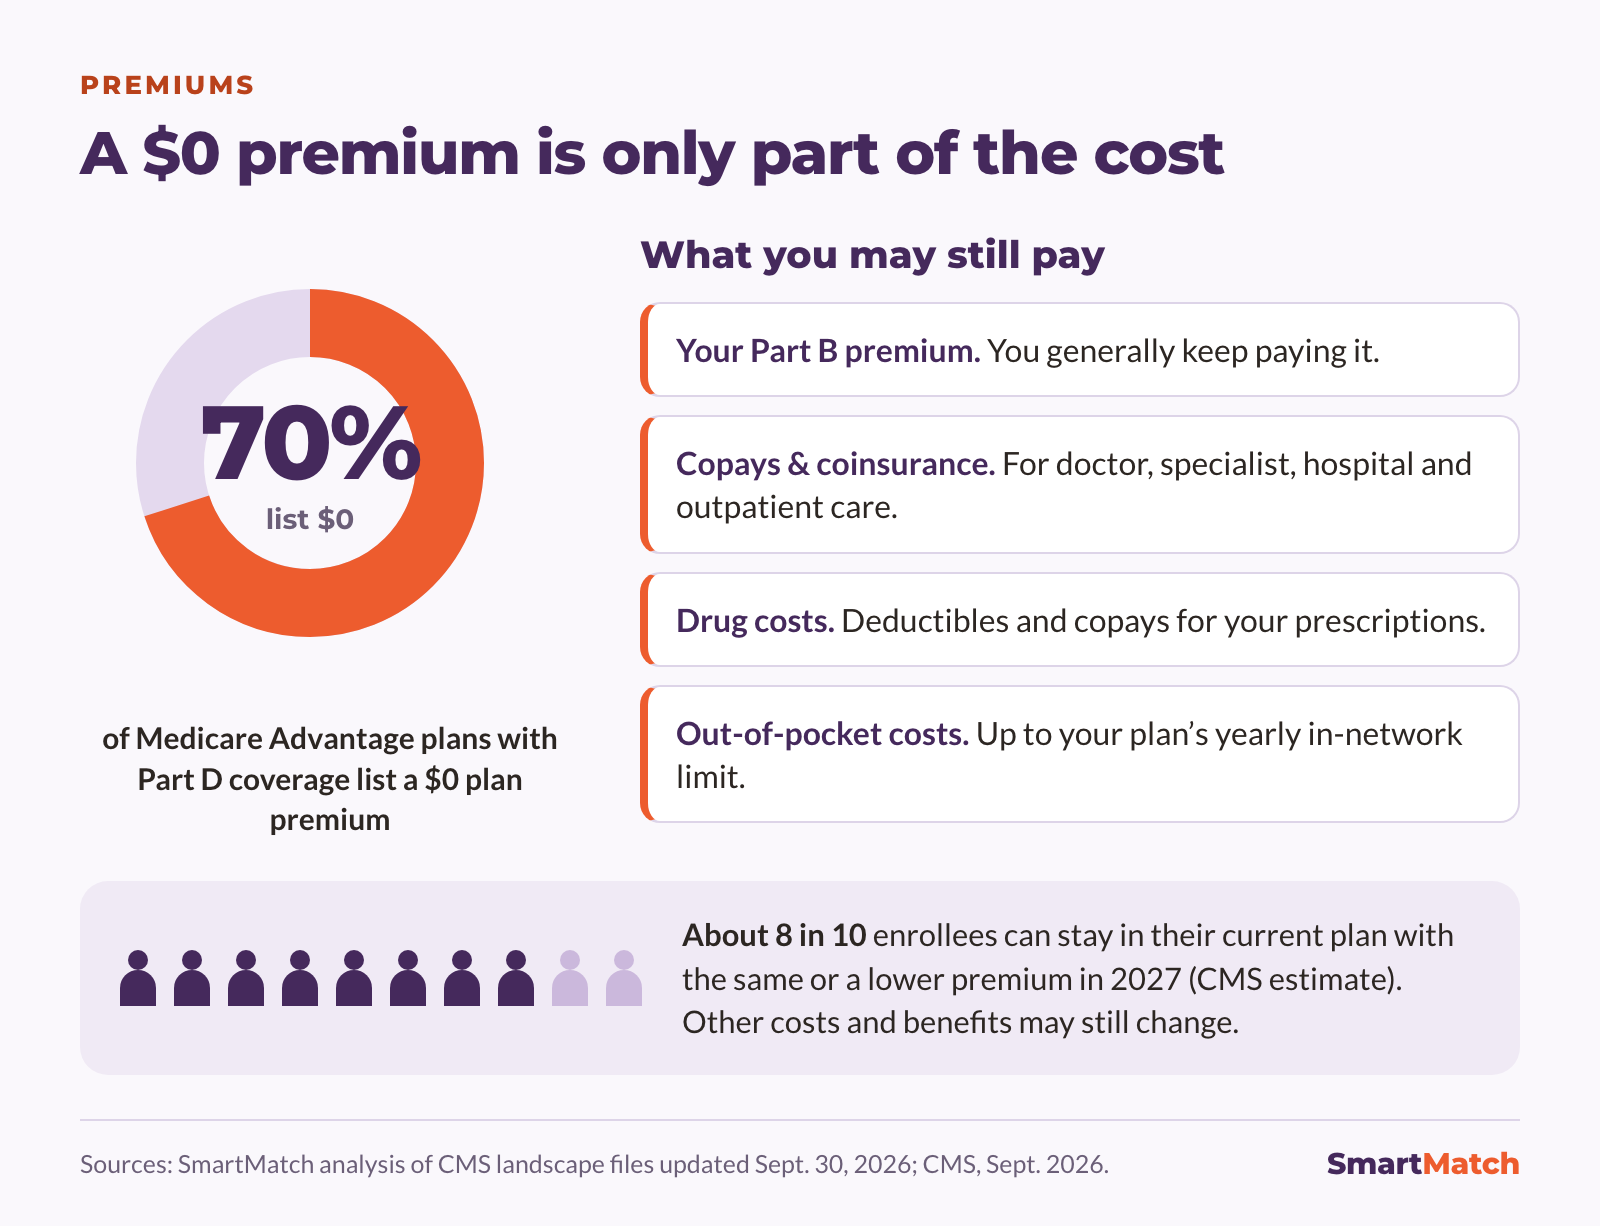
A $0 premium is only part of the cost. About 70% of Medicare Advantage plans with Part D coverage list a $0 plan premium. You may still pay your Part B premium, copays and coinsurance for doctor, specialist, hospital and outpatient care, prescription deductibles and copays, and out-of-pocket costs up to your plan’s yearly in-network limit. CMS estimates about 8 in 10 enrollees can stay in their current plan with the same or a lower premium in 2027; other costs and benefits may still change.

Out-of-pocket limits are moving higher in many plans

Every Medicare Advantage plan has a yearly limit on what you pay for covered Part A and Part B services. This is commonly called the maximum out-of-pocket, or MOOP, limit. The limit does not include every expense, such as your Part B premium or most prescription drug costs.

The median in-network MOOP in the CMS landscape file increased from $6,500 in 2026 to $7,100 in 2027.
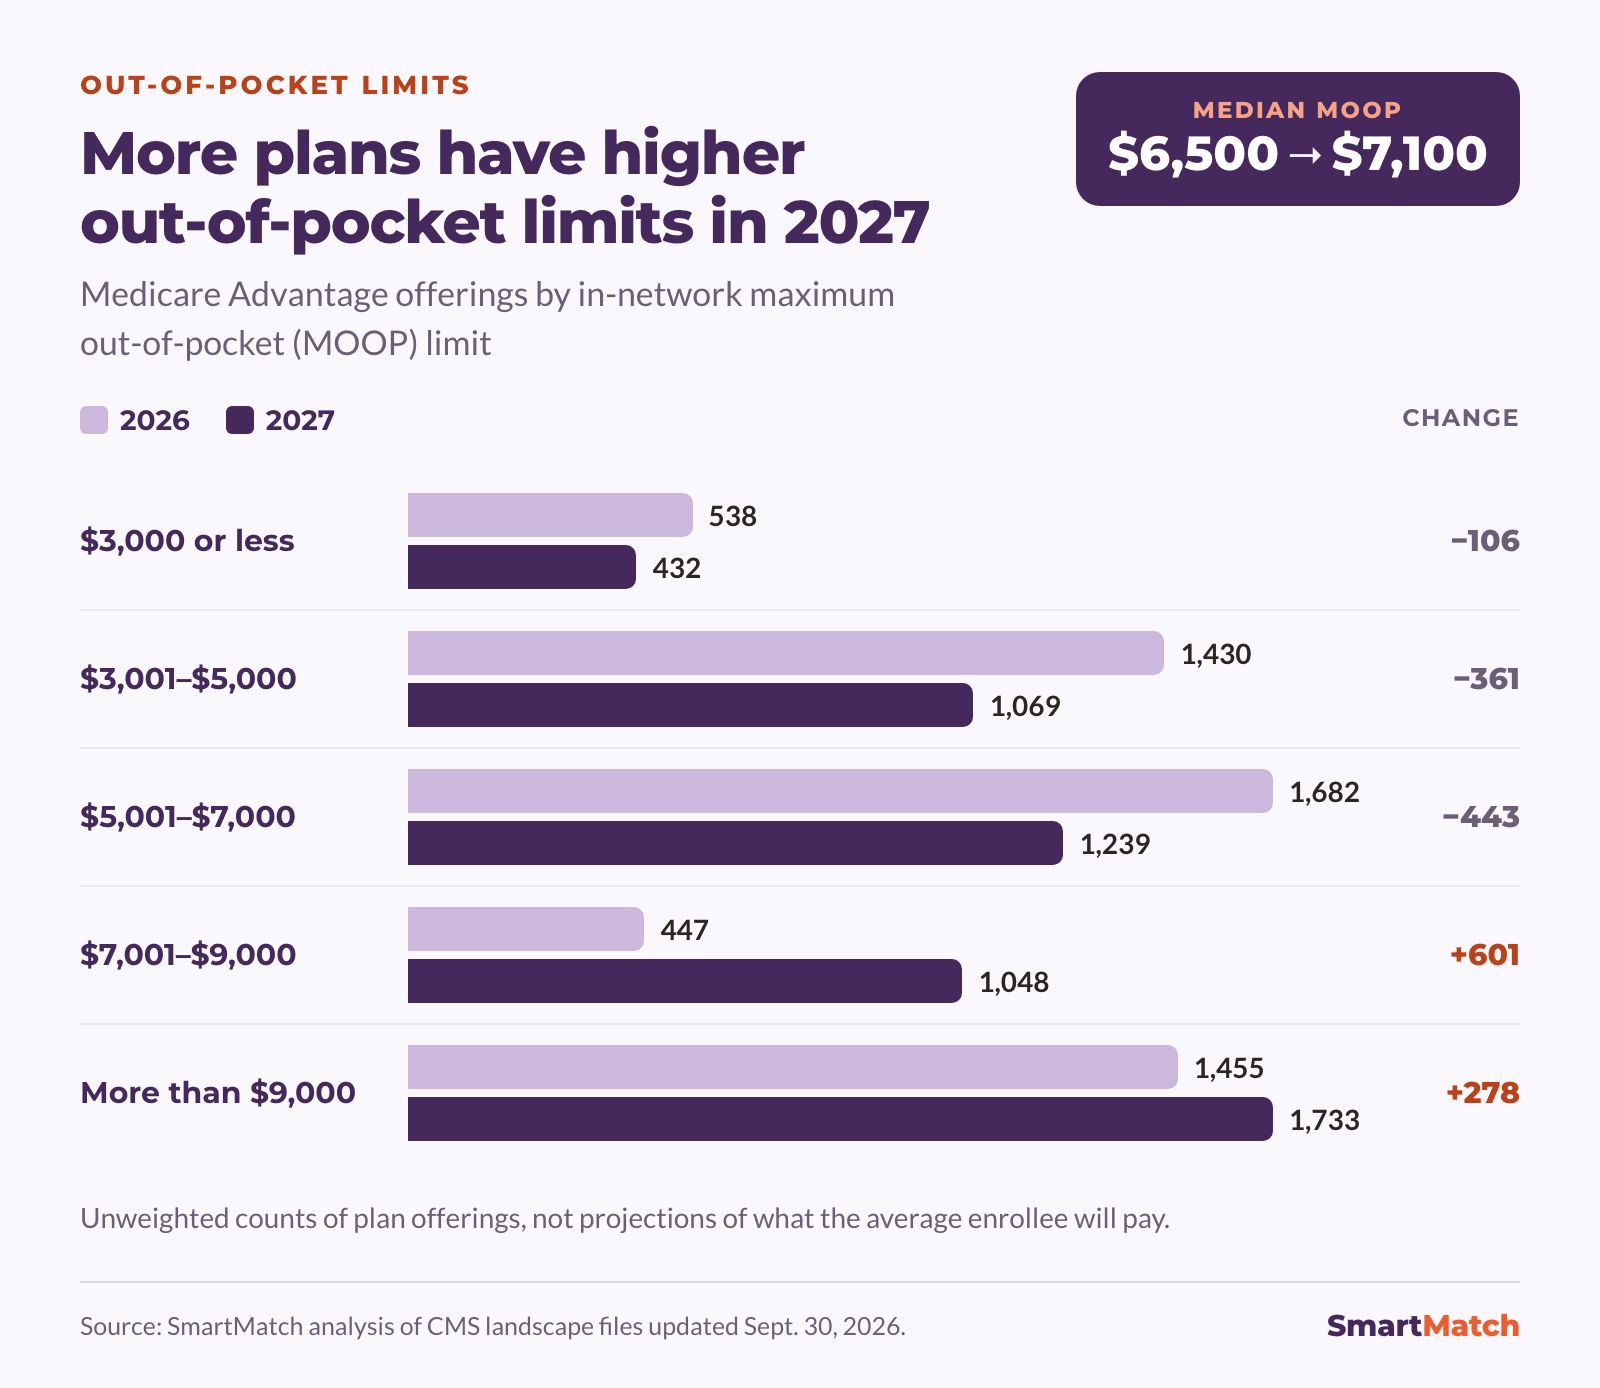
Bar chart of Medicare Advantage offerings by in-network maximum out-of-pocket limit, 2026 versus 2027. $3,000 or less: 538 to 432. $3,001 to $5,000: 1,430 to 1,069. $5,001 to $7,000: 1,682 to 1,239. $7,001 to $9,000: 447 to 1,048. More than $9,000: 1,455 to 1,733. The median limit rose from $6,500 to $7,100. These are unweighted counts of plan offerings, not projections of what the average enrollee will pay.
See the numbers
In-network MOOP range2026 offerings2027 offerings
$3,000 or less538432
$3,001–$5,0001,4301,069
$5,001–$7,0001,6821,239
$7,001–$9,0004471,048
More than $9,0001,4551,733

What this means for you: Two plans with the same premium can expose you to very different costs when you use care. Compare the MOOP limit along with the copays for services you are likely to use.

Prescription drug deductibles are higher in many MA-PD plans

Among Medicare Advantage plans with prescription drug coverage, the unweighted average annual drug deductible in the CMS landscape file rose from about $434 in 2026 to $525 in 2027.
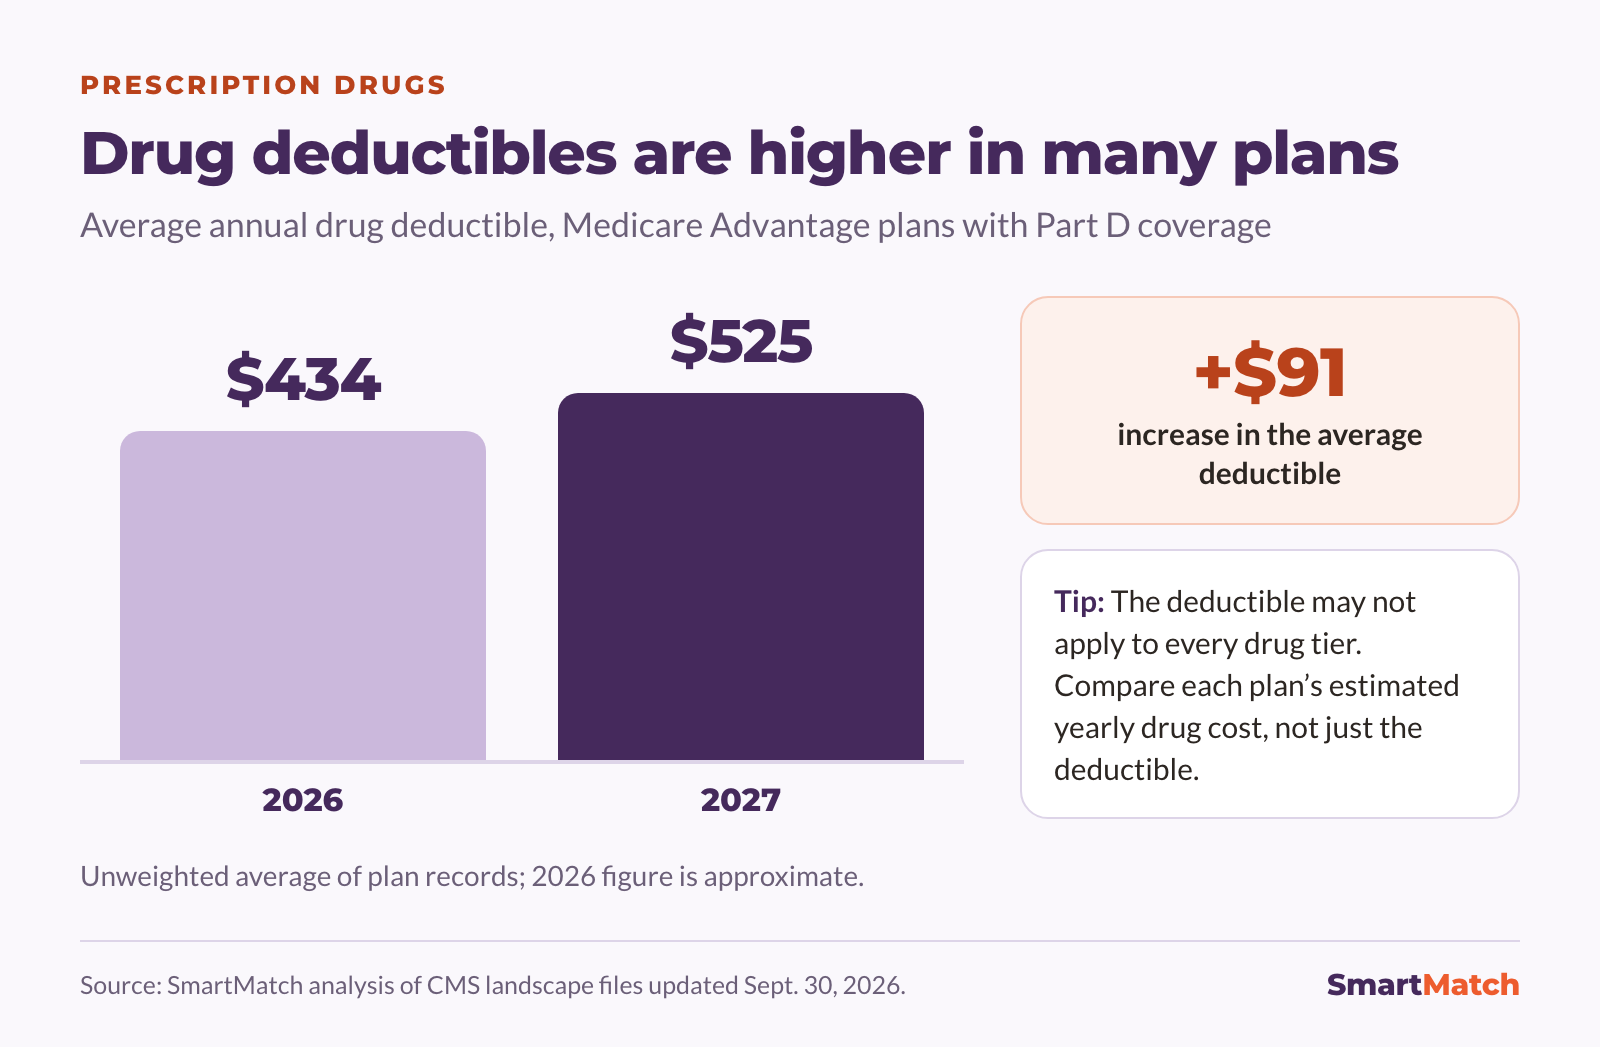
Column chart: the average annual drug deductible in Medicare Advantage plans with Part D coverage rose from about $434 in 2026 to $525 in 2027, an increase of about $91. The deductible may not apply to every drug tier, so compare each plan’s estimated yearly drug cost.

The deductible may not apply to every drug tier. Some plans cover certain generic or preferred drugs before you meet the deductible.

What this means for you: Enter each medication in Medicare Plan Finder and compare estimated annual costs—not just the deductible. Check the formulary, drug tier, participating pharmacies and any prior authorization or step therapy requirements.

Special Needs Plan options are expanding

Special Needs Plans, or SNPs, are Medicare Advantage plans designed for defined groups of people, such as people who have both Medicare and Medicaid, live in certain institutions or have specific chronic conditions.
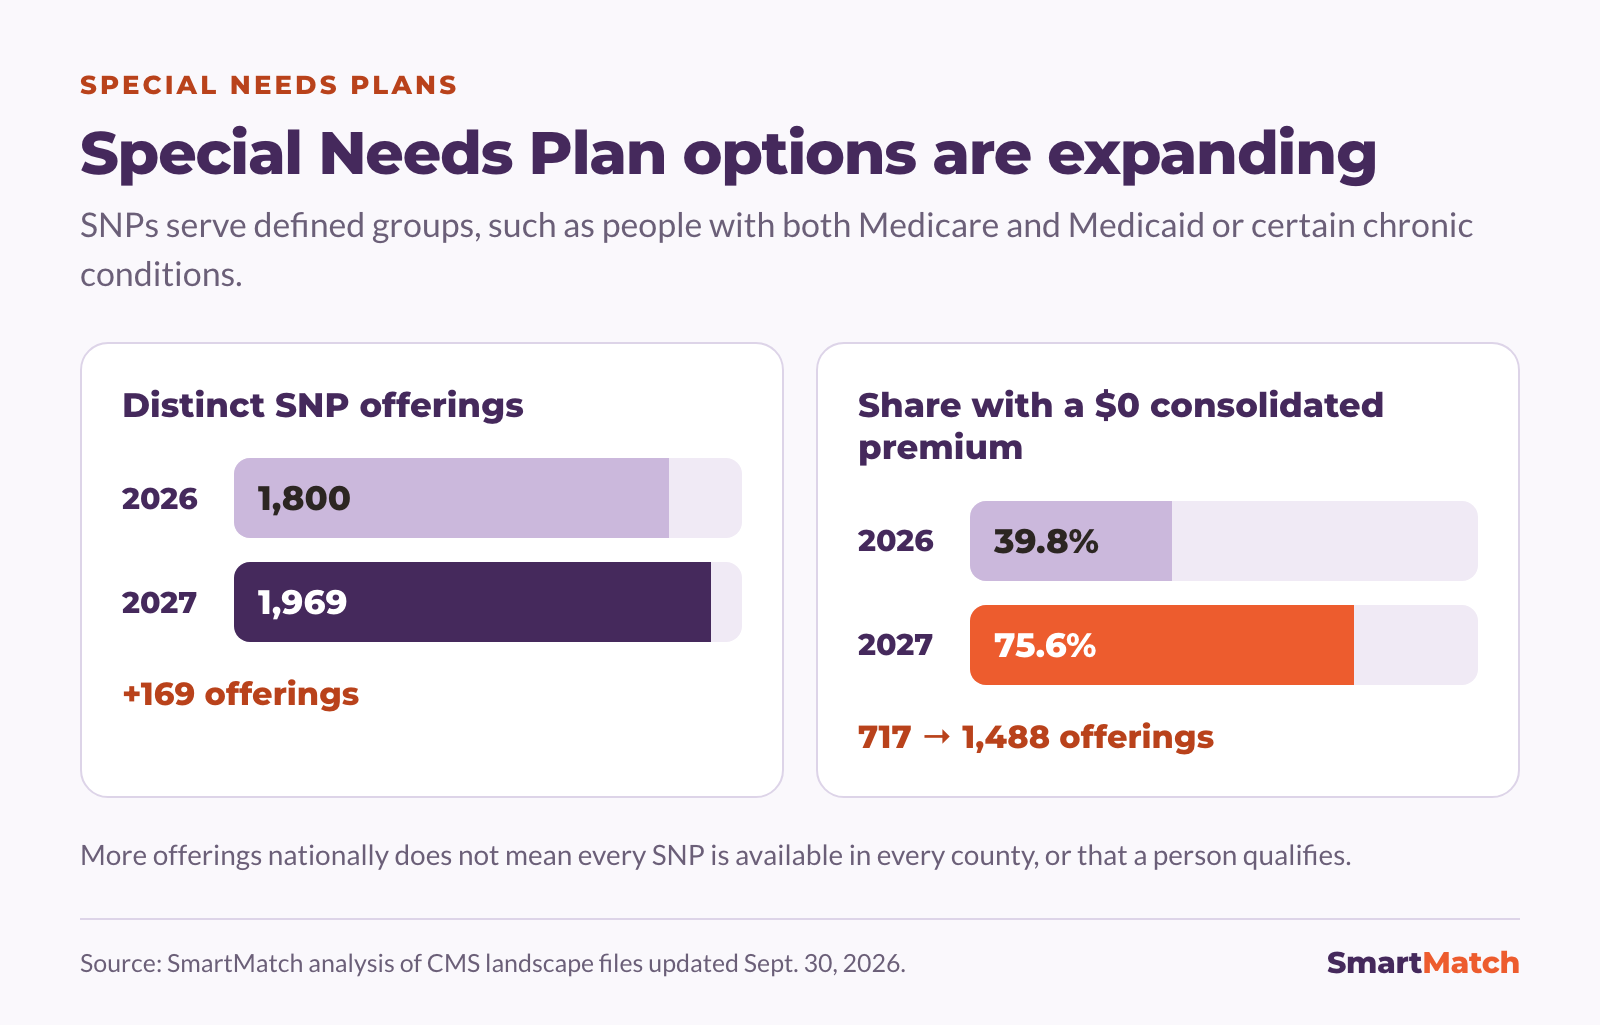
Special Needs Plan options are expanding. Distinct SNP offerings rose from 1,800 in 2026 to 1,969 in 2027, an increase of 169. The share of SNP offerings with a $0 consolidated premium rose from 39.8% (717 offerings) to 75.6% (1,488 offerings).
See the numbers
SNP measure20262027
Distinct SNP offerings1,8001,969
Offerings with a $0 consolidated premium717 (39.8%)1,488 (75.6%)

Benefits and eligibility requirements vary. A larger number of SNP offerings does not mean every option is available in every county or that a person qualifies for a particular plan.

What this means for you: If you think a SNP may fit your circumstances, review the plan’s eligibility rules, provider network, drug coverage and service area with Medicare or a licensed insurance agent.

Carrier participation is changing

The CMS landscape file shows that some parent organizations expanded their number of Medicare Advantage offerings while others reduced them.
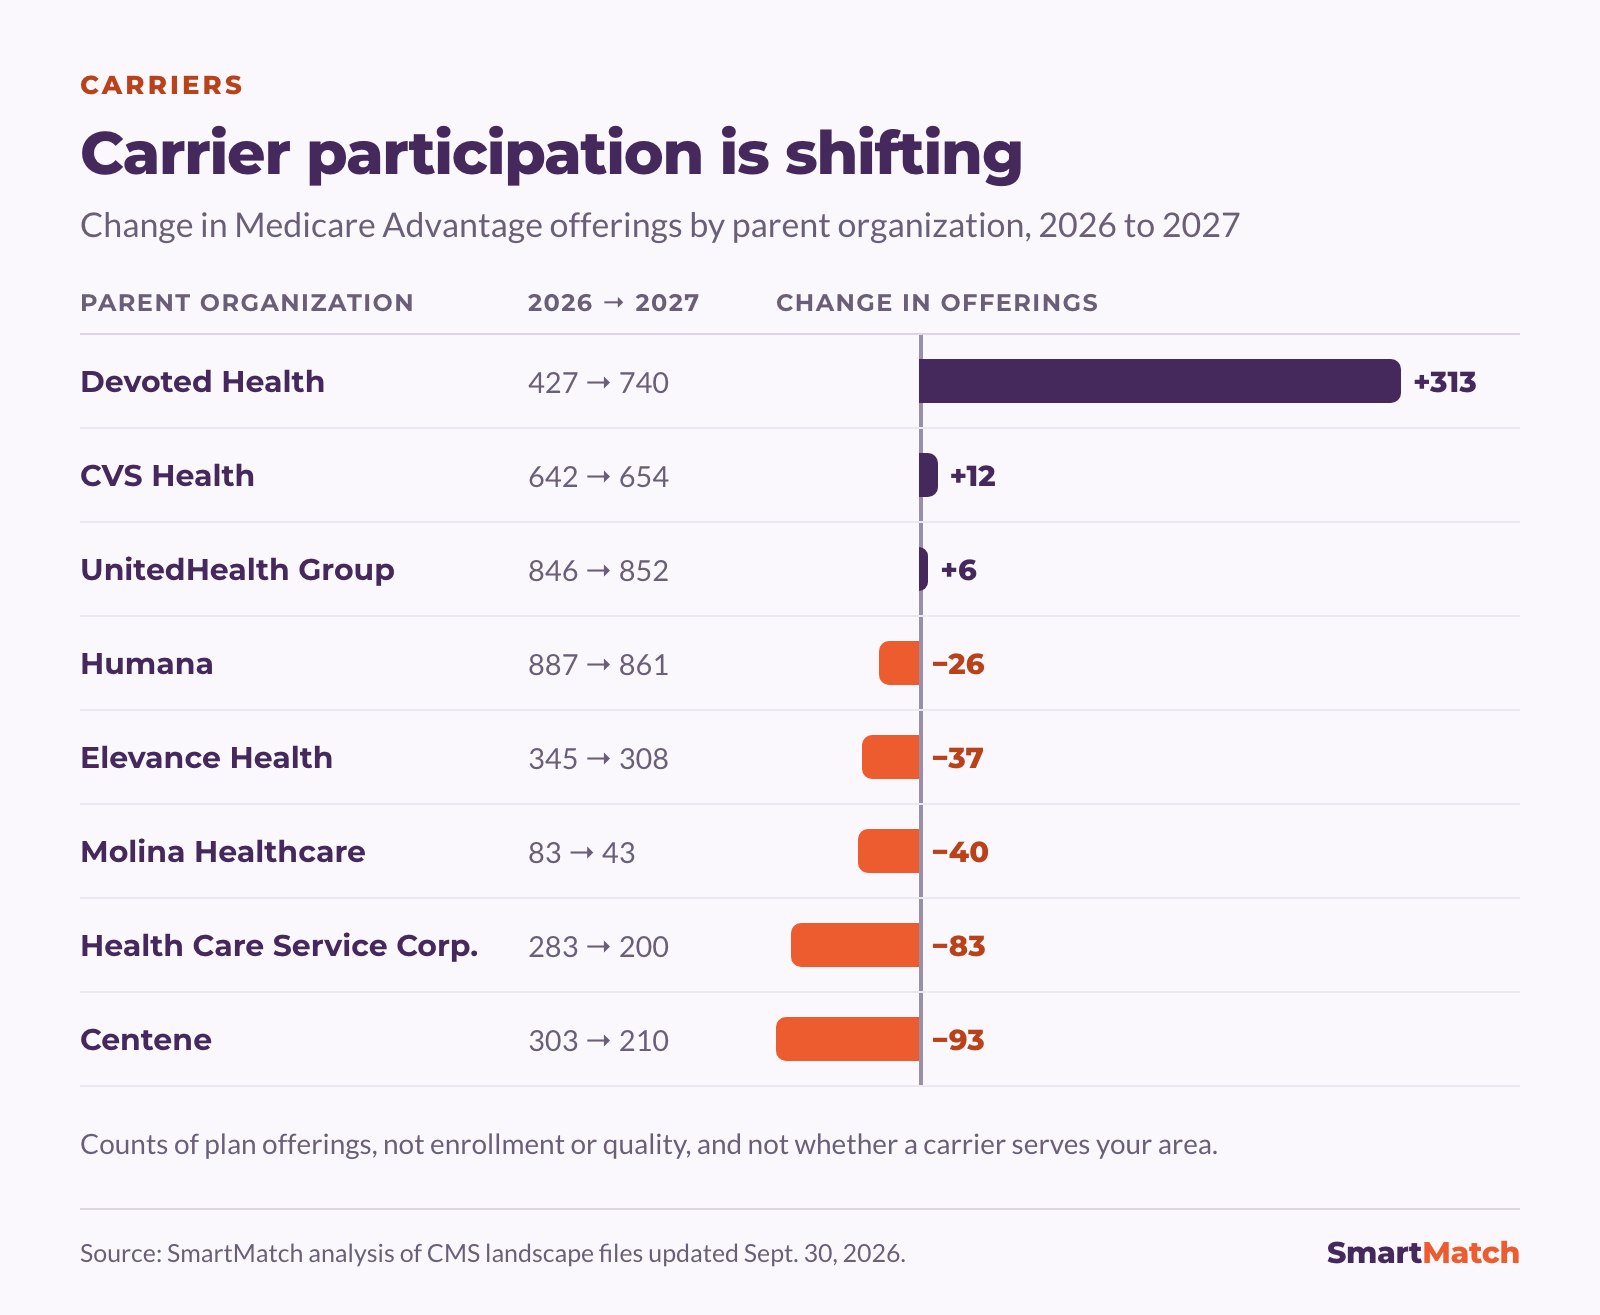
Bar chart of the change in Medicare Advantage offerings by parent organization from 2026 to 2027. Devoted Health 427 to 740, up 313. CVS Health 642 to 654, up 12. UnitedHealth Group 846 to 852, up 6. Humana 887 to 861, down 26. Elevance Health 345 to 308, down 37. Molina Healthcare 83 to 43, down 40. Health Care Service Corporation 283 to 200, down 83. Centene 303 to 210, down 93.
See the numbers
Parent organization2026 MA offerings2027 MA offeringsChange
Humana887861-26
UnitedHealth Group846852+6
Devoted Health427740+313
CVS Health642654+12
Elevance Health345308-37
Centene303210-93
Health Care Service Corporation283200-83
Molina Healthcare8343-40

These counts describe plan offerings, not enrollment, quality or whether a carrier serves your area. Growth does not make one carrier a better fit, and contraction does not mean every plan from that carrier is ending.

What this means for you: Read your Annual Notice of Change and Evidence of Coverage. Confirm that your plan is continuing in your county and that your doctors, hospitals, prescriptions and preferred pharmacies will still be covered as expected.

What to do before Medicare Open Enrollment

You can compare 2027 plans beginning October 1. Medicare Open Enrollment runs from October 15 through December 7, 2026, and changes made during this period generally take effect January 1, 2027.
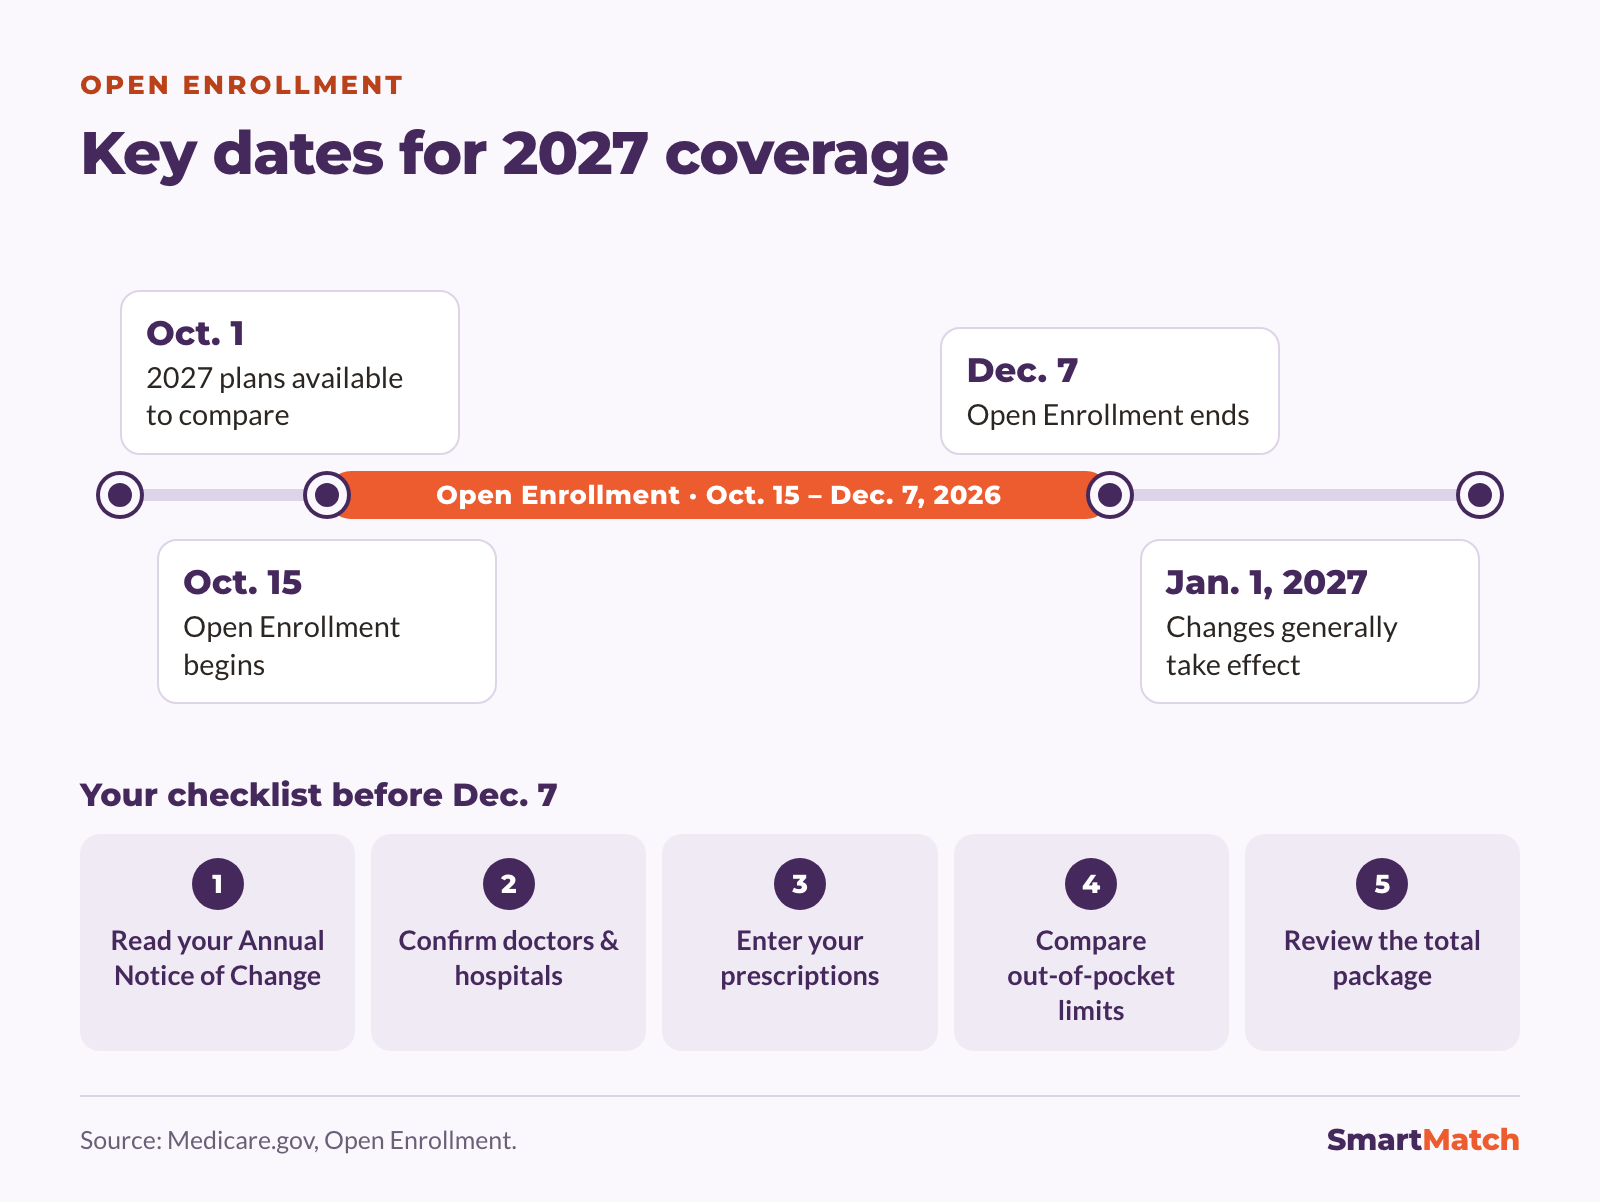
Timeline of key dates for 2027 coverage: October 1, 2027 plans available to compare. October 15, Open Enrollment begins. December 7, Open Enrollment ends. January 1, 2027, changes generally take effect. Checklist before December 7: read your Annual Notice of Change, confirm doctors and hospitals, enter your prescriptions, compare out-of-pocket limits, and review the total package.

Use Medicare Plan Finder for an official comparison, or connect with a licensed SmartMatch insurance agent for help reviewing Medicare Advantage options available in your area.

Methodology

Unless identified as a CMS projection, figures above are SmartMatch calculations from distinct contract-plan-segment records in the CMS landscape files updated September 30, 2026. The analysis excludes Medicare Cost plans and standalone Part D plans. Averages and distributions calculated from plan records are unweighted and do not represent enrollment-weighted beneficiary experience. Landscape data can change as contracts are finalized.


What to do before Medicare Open Enrollment

  1. Read your Annual Notice of Change

    Look for changes to premiums, copays, benefits, drug coverage and service area.

  2. Confirm your doctors and hospitals

    Provider networks can change from year to year.

  3. Enter your prescriptions

    Do not evaluate a plan on premium alone.

  4. Review the total package

    Consider the services and benefits you expect to use, not simply the longest benefit list.

Common questions

Will my Medicare Advantage plan stay the same in 2027?

National plan availability is stable, but your current plan’s costs, benefits and network can change. Read your Annual Notice of Change and confirm your plan continues in your county.

Is a $0-premium Medicare Advantage plan free?

No. About 70% of Medicare Advantage plans with Part D coverage list a $0 plan premium, but you generally keep paying your Medicare Part B premium, plus copays, drug costs and anything up to the plan’s yearly out-of-pocket limit.

What is a Medicare Advantage out-of-pocket limit?

It is the yearly limit on what you pay for covered Part A and Part B services, often called the maximum out-of-pocket or MOOP. It does not include your Part B premium or most prescription drug costs. In the CMS landscape file, the median in-network limit rose from $6,500 in 2026 to $7,100 in 2027.

Are there fewer Medicare Advantage plans for 2027?

The number is relatively stable. The CMS landscape file updated September 30, 2026 shows 5,522 distinct Medicare Advantage offerings, down 31 from 2026. CMS says more than 99% of people with Medicare will have access to at least one plan.

When can I enroll in a 2027 Medicare Advantage plan?

You can compare 2027 plans beginning October 1. Medicare Open Enrollment runs from October 15 through December 7, 2026, and changes made then generally take effect January 1, 2027.

Compare 2027 Medicare Advantage plans where you live

A licensed SmartMatch insurance agent can walk through the plans available in your area. There is no obligation to enroll.

Talk with an agent
Or call a licensed insurance agent 1-888-411-7647 TTY: 711 Mon. – Fri., 7:30 AM – 5 PM CT
SmartMatch Insurance Agency, LLC
Corporate Office:
120 W. 12th St.
Suite 1700
Kansas City, Missouri 64105

Business Hours:
Monday – Friday
7:30am – 5pm CT
Stay Connected

This is a solicitation for insurance. Not connected with or endorsed by the U.S. government or the federal Medicare program. SmartMatch Insurance Agency and its divisions are licensed to sell insurance products in all 50 states and DC. Callers will be connected with a licensed insurance agent who can enroll you into a Medicare Advantage, Prescription Drug (Part D) and Medicare Supplement insurance plan.

We do not offer every plan available in your area. Currently we represent 29 organizations which offer 3,502 products in your area. Please contact Medicare.gov, 1-800-MEDICARE (24 hours a day/7 days a week), or your local State Health Insurance Program to get information on all of your options. The plans we represent do not discriminate on the basis of race, color, national origin, age, disability, or sex. Not all plans offer all benefits. Benefits may vary by carrier and location. Limitations and exclusions apply. No obligation to enroll. SmartMatch Insurance Agency represents Medicare Advantage HMO, HMO SNP, PPO, PPO SNP, and PDP organizations that have a Medicare contract. Enrollment in any plan depends on contract renewal.

PLEASE NOTE: Medicare Supplement insurance is available to those age 65 and older enrolled in Medicare Parts A and B and, in some states, to those under age 65 eligible for Medicare due to disability or End-Stage Renal Disease (ESRD). Enrollment in a plan may be limited to certain times of the year unless you qualify for a Special Enrollment Period or you are in your Medicare Initial Enrollment Period.

Privacy Policy | Terms & Conditions

MULTIPLAN_SMIAWEBSITE26_M

Please log in to view assigned tenants.
